



caucasian hand rolling two red dice representing how pharmacy benefit costs are risky.

Why Would Employers “Roll the Dice” on Their Rx Benefit Program?

Pharmacy benefit costs now account for 25% of healthcare spending and are projected to increase by 12% nationally through 2027. Meanwhile, the public sector in the Northeast is facing significantly higher trends of 18% to 20%. These unprecedented numbers are being largely driven by the skyrocketing use of GLP-1s, oncology medications, and increased usage of high-cost specialty drugs.

The PBM Gamble: Enticing Rebates, Hidden Risks

Despite these alarming trends, many plan sponsors remain in traditional self-funded arrangements with limited stop-loss coverage. Why? Because rebates continue to be the carrot these PBMs dangle in front of plan sponsors with promises of substantial money to offset their claims. The reality? Plan sponsors end up blowing through their fiscal budget, especially in the first year when they only receive two rebate payments. The cause? Because PBMs are not financially responsible for actual pharmacy costs, they often rely on projected rebates, discounts, and clinical program performance savings to support their cost projections. When those savings fall short, the financial risk remains with the plan sponsor.

Do those same PBM’s guarantee actual claim dollars? Unfortunately, no. Here’s what’s really happening:

  • PBMs drive up rebate values by directing members to higher cost brand and specialty drugs. So yes, the rebates sure do look enticing, but those rebates are built off the back of tentative guarantees and off claims where higher rebates do not result in the lowest net cost to the plan sponsor.
  • Empty promises claiming 20% savings through “clinical programs” or “better network pricing” are easy to make when there are no guarantees or validation of such savings. The reality is that even if some PBMs guarantee clinical savings on their program, they still don’t have any financial responsibility to guarantee the plan sponsor’s actual claim costs for the given contract year. The plan sponsor bears that risk.
  • Rebate payments won’t be enough to offset plan sponsor claim spending. The first quarterly rebate payment in a traditional self-funded arrangement won’t be paid to plan sponsors until 120-150 days after each calendar year quarter closes, potentially resulting in only one to two rebate payments in the first year. Additionally, these PBM’s may identify several financial caveats in their proposals which can greatly reduce the guaranteed value of the rebate payments, such as federal and state regulatory requirements that impact rebates like the Inflation Reduction Act, an increase in biosimilar products to the marketplace, most favored nation pricing, etc.

Stop Rolling the Dice

In light of increasing cost trends, traditional PBM’s turn to contract transparency.  In contrast, Benecard offers price transparency. The plan sponsor knows their spend exactly, no guess work, no projections, and no rolling the dice. Our unique funding arrangement is fully aligned with plan sponsors’ financial and budgetary goals.

Benecard’s Fixed-Rate Program Includes:

  • 100% risk protection – Plan sponsors pay nothing more than their monthly fixed rate, no matter how high claims may exceed those charges. There is no “true-up” or reconciliation either.
  • Return-of-savings program – Plan sponsors receive 100% of savings when claims perform better than expected (meaning Benecard’s margin of return is capped).
  • Upfront rebates – 100% of our rebates are floated and factored into our fixed guaranteed monthly program charges starting in month one, giving plan sponsors an upfront cash flow advantage other PBMs can’t offer.
  • Solutions that work for clients – Plan sponsors retain 100% autonomy of their plan design & benefits.

Ready to Learn More?

Watch our video to learn how our fixed-rate prescription benefit program provides the best way to take the risk out of pharmacy benefits.

In today’s pharmacy landscape, managing benefit costs shouldn’t be a gamble. Let us show you how Benecard’s proven approach can help plan sponsors beat the odds, control costs, and achieve greater budget certainty. Reach out to talktous@benecard.com to start the conversation.

Sources:

2027 Employer Healthcare Strategy Survey: Executive Summary: https://temp.businessgrouphealth.org/resources/2027-employer-healthcare-strategy-survey-executive-summary

2026 Milliman Medical Index: https://media.milliman.com/v1/media/edge/images/millimaninc5660-milliman6442-prod27d5-0001/media/Milliman/PDFs/2026-Articles/2026_Milliman-Medical-Index.pdf

Other Benecard Articles: If you enjoyed reading this article you might like to check out this one: https://www.benecard.com/get-the-whole-picture-on-level-funding-look-at-the-advantages-and-limitations/


Photo of Kevin Kroll, COO, Benecard Services, LLC, Prescription Benefit Administrator

The Hidden Gamble in Self-Funded Pharmacy Benefits

Employers today face growing challenges in accurately forecasting and budgeting for health benefit expenses. Pharmacy benefits are no exception.

In many traditional self-funded PBM arrangements, employers may not know their true pharmacy costs until months after claims are incurred, once rebates and other financial guarantees are reconciled. That uncertainty can make budgeting and forecasting increasingly difficult.

Our COO of Benecard Services, Kevin Kroll, was recently interviewed by BenefitsPRO. In the article he discusses the hidden risks behind enticing rebate promises and why pharmacy cost predictability deserves a closer look.

Read the article: Gambling with Your PBM Self-Funded Program: Enticing Rebates but Hidden Risks. If you don’t have a BenefitsPRO account, click here for the PDF version.

Male teacher reading paperwork in classroom.

NJ SEHBP 2027 Rates Approved: What Comes Next for School Districts?

After nearly two months of deadlocked votes, the New Jersey School Employees’ Health Benefits Commission approved 2027 premium rates for active school employees on September 25th, including increases of up to 34%. The approval provides a path forward for the 2027 plan year, but questions posed by New Jersey’s Department of Treasury about both the SHBP and SEHBP’s long-term financial viability remain tentative at best.

Stability Matters

For many New Jersey school districts, health benefits continue to create havoc on their budgets due to significant reductions in rebate dollars, growing marketplace and utilization of high-cost specialty drugs and the continued financial impact of GLP-1 drugs.

Prescription drug costs are an important part of that equation. Benecard’s fixed-rate prescription benefit can help provide greater budget predictability by reducing exposure to fluctuations in pharmacy claims while incorporating 100% risk protection, return of savings benefits, and our clinical management expertise.

As school districts navigate continued uncertainty within the SEHBP, evaluating benefit strategies that provide greater stability may be an important part of preparing for the years ahead.

For more information about Benecard’s fixed-rate prescription benefit model, contact Richard Van Noord, Vice President of Sales, at Richard.VanNoord@benecard.com or (609) 651-5412.

Sources:

Breaking News: NJ SEHBP 2027 Rate Decision Delay Creates Urgent Planning Concerns – Benecard
https://www.benecard.com/breaking-news-nj-sehbp-2027-rate-decision-delay-creates-urgent-planning-concerns/

After state warning, NJ panel approves 34% health premium hike for teachers • New Jersey Monitor
https://newjerseymonitor.com/2026/09/25/nj-health-premium-increase-school-workers-approved

Structural Financial Challenges Notification
https://www.nj.gov/treasury/pensions/documents/pdf/Structural-Financial-Challenges-SHBP-LG.pdf

Teachers looking stressed while reviewing the computer screen

Breaking News: NJ SEHBP 2027 Rate Decision Delay Creates Urgent Planning Concerns

As we have been reporting, the New Jersey School Employees’ Health Benefits Commission (Commission) has been unable to approve the NJ Plan Year 2027 premium rates for active employees participating in the School Employees’ Health Benefits Program (SEHBP). After deadlocked votes on July 27th, August 19th, and September 3rd, 2026, the Commission is scheduled to vote again on September 28th.

Will There Be an NJ SEHBP Plan in 2027?

While the deferred approval has already confirmed delays for open enrollment, the more significant issue is the State’s warning. If the Commission fails to approve Plan Year 2027 premium rates on September 28th, SEHBP will not be an available option for employers to provide health benefits beginning January 1, 2027. Employers should begin evaluating alternative benefit options and consult their own legal counsel regarding any potential implications for their IRC Section 125 cafeteria plans.

Organizations participating in the SEHBP should start considering potential changes to their 2027 health benefit strategy. If you would like to explore available options or discuss how Benecard can provide support, contact Richard Van Noord, Vice President of Sales, at Richard.VanNoord@benecard.com or (609) 651-5412.

Benecard will continue to monitor developments and provide updates as new information on the SEHBP 2027 rate actions becomes available.

Sources:

SEHBP Financial Challenges Persist Amid Unresolved Premium Rate Decisions – Benecard:

State of NJ – Department of the Treasury – NJDPB | Certifying Officer Letters:

NJ Treasury – Division of Pensions & Benefits

https://www.nj.gov/treasury/pensions

Plan Year 2027 Rate Renewal Reports:                                

https://www.nj.gov/treasury/pensions/rate-renewal.shtml

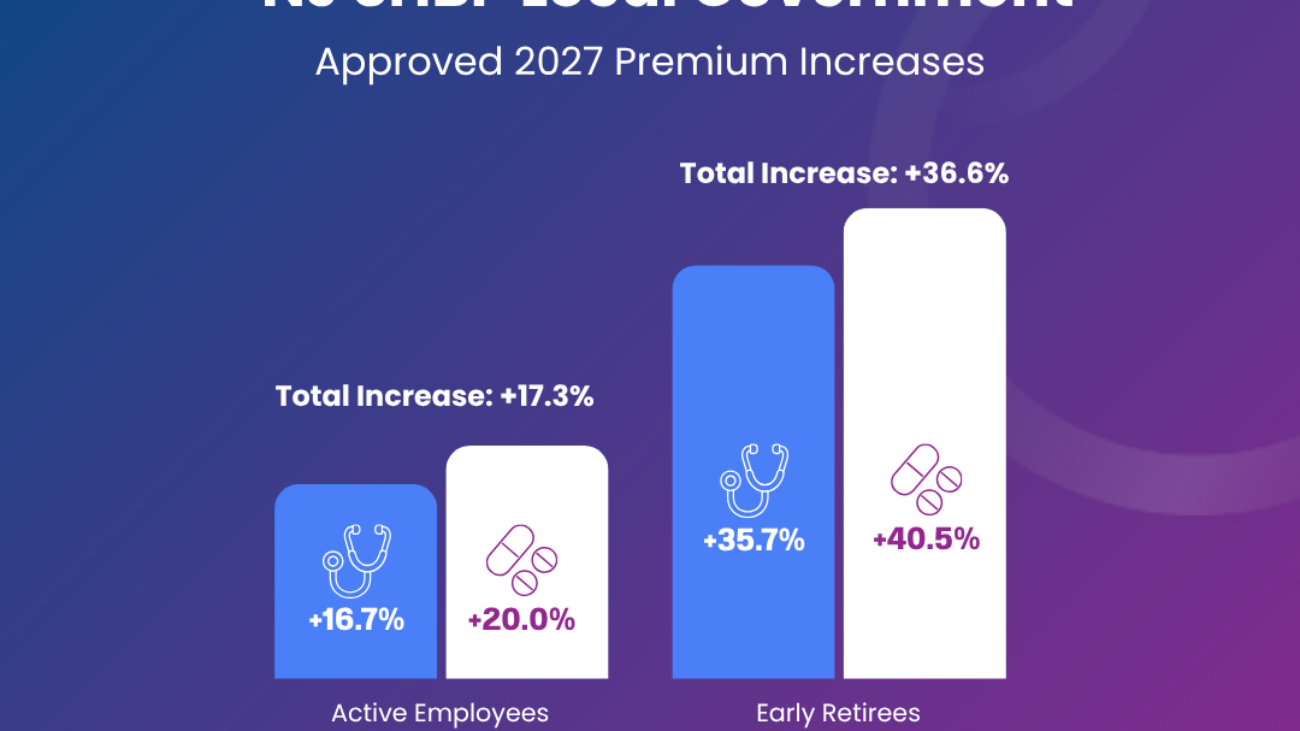
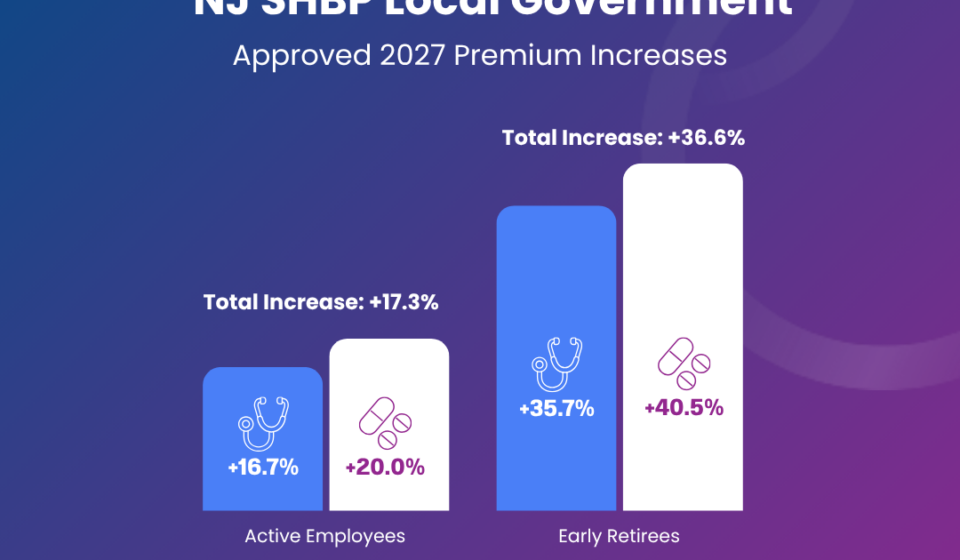
NJ SHBP Local Government 2027 approved annual healthcare premiums graph. This includes both medial and prescription drug benefit increases.

Update: NJ SHBP and SEHBP Rate Renewals – Where Do They Stand?

On September 3rd, the NJ School Employees’ Health Benefits (SEHBP) and State Health Benefits Programs (SHBP) resumed discussions to finalize the renewal rates for the 2027 plan year, with only the SHBP coming to a resolution.

The SHBP approved the combined rate recommendation for Local Government (LG) Actives, Early Retirees, and Medicare Retirees at a 22.1% overall premium increase — with a portion of the increase slated to repay prior funding obligations and rebuild depleted reserves, rather than just to cover projected healthcare costs. 

SHBP Local Government Approved Rate Renewals:

  • Active Populations: +17.3% Total Increase
    • +16.7% increase for medical
    • +20.0% increase for prescription
  • Early Retiree Populations: +36.6% Total Increase
    • +35.7% increase for medical
    • +40.5% increase for prescription

The SEHBP on the other hand, failed to approve any rates for the 2027 renewal year for a second time. The Commission deadlocked in a 4-4 vote on the recommended increases and agreed to reconvene in 2 weeks for another vote.

Benecard will continue to update you on any further developments with the final SEHBP 2027 rate actions as more information is released.

In the meantime, for organizations participating in the SHBP or SEHBP, now is the time to consider whether your current approach is delivering the cost control and financial certainty you need. Contact Richard Van Noord, Vice President of Sales, at Richard.VanNoord@benecard.com or (609) 651-5412 to explore what’s possible.

Sources:

NJ Panels OK Rate Hike for Public Worker Health Plans Deadlock on Increase for Teachers:

https://newjerseymonitor.com/2026/09/03/nj-panels-ok-rate-hike-for-public-worker-health-plans-deadlock-on-increase-for-teachers

Aon’s SHBP “Plan Year 2027 Rate Setting Recommendation Analysis” Local Government Employee Group Report (as approved on 9/3/2026):

https://nj.gov/treasury/pensions/documents/hb/rate-renewal/py2027-rate-setting-analysis-local.pdf

Plan Year 2027 Rate Renewal Reports:

https://www.nj.gov/treasury/pensions/rate-renewal.shtml

SEHBP Financial Challenges Persist Amid Unresolved Premium Rate Decisions – Benecard:

New Jersey state capitol building in Trenton

SEHBP Financial Challenges Persist Amid Unresolved Premium Rate Decisions

The NJ School Employees’ Health Benefits Commission (SEHBC) meeting on August 19th brought no final resolution for the School Employees’ Health Benefits Program (SEHBP), which remains under significant financial strain amid a proposed 32.4% increase in medical premiums and a 45.5% increase in prescription drug premiums for active employees.

The only update stems from the NJ School Employees’ Health Benefits Commission approving revised retiree rate recommendations, but those recommendations have not been advertised or finalized as of yet. Meanwhile, the Commission remains deadlocked on a 4-4 vote to finalize the 2027 active population premium increases. This vote came four weeks after the commission failed to finalize the active population premium increases on July 27th, citing the need to review cost saving options. Aon presented several cost saving considerations for both the medical and prescription plans, but the NJ State Plan Design Committee (PDC), not the SEHBC, is responsible for plan changes. It was further noted that Chapter 44, which relates to the NJ Educators Health Plan (EHP) and Garden State Health Plan (GSHP), bars any changes until 2028.

The SEHBC will reconvene on September 3rd for another vote, though it’s unclear what, if anything, will have changed by then. Benecard is keeping a close eye on this subject and will continue to update you as new information becomes available.

In the meantime, plan sponsors enrolled in either the SEHBP or SHBP, can be proactive by starting to look into alternative options. Contact Richard Van Noord, our Vice President of Sales, at Richard.VanNoord@benecard.com or (609) 651-5412 to learn how Benecard’s fixed-rate prescription benefit model can offer greater predictability and stability.

Sources:

NJ Teachers Face a Health Insurance Nightmare – And No One Can Stop It
https://nj1015.com/nj-teachers-health-insurance-increase

NJ SHBP & SEHBP 2027 Rate Recommendations Released – What You Should Know
https://www.benecard.com/nj-shbp-sehbp-2027-rate-recommendations-released-what-you-should-know/

Plan Year 2027 Rate Renewal Reports (recommendations):                                
https://www.nj.gov/treasury/pensions/rate-renewal.shtml

Aon’s SHBP “Plan Year 2027 Rate Setting Recommendation Analysis” Local Government draft report:
https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/py2027-rate-setting-analysis-local.pdf

Aon’s “2027 SHBP Rate Setting Analysis” draft report presentation:
https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/shbp-2027-rate-setting-analysis.pdf

View Aon’s SEHBP “Plan Year 2027 Rate Setting Recommendation Analysis” Education draft report:
https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/py2027-rate-setting-analysis-education.pdf

Aon’s “2027 SEHBP Rate Setting Analysis” draft report presentation:
https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/sehbp-2027-rate-setting-analysis.pdf

Image of a man and woman split screen left side image of woman and man losing hair. The right side of the image show regrowth of hair on both woman and man

The Next GLP-1? Why Hair Loss Drugs Could Be the Pharmacy Trend No One Saw Coming

Just as plan sponsors begin to gain their footing on GLP-1 management strategies, another emerging category is quietly advancing through the pipeline: hair loss treatment.

Historically, treatment options for pattern hair loss had limited choices at a modest costs, ranging from topical minoxidil (Rogaine®), to oral finasteride, and various off-label therapies. However, a new generation of non-specialty (VDPHL01) and specialty (PP405) medications are being developed that could significantly improve outcomes for both men and women experiencing hair loss.

Why Should This Concern Plan Sponsors?

Pattern hair loss affects approximately 80 million adults in the United States1, creating substantial utilization potential if these therapies receive FDA approval and gain market acceptance.

None of the medications discussed below are FDA-approved at this time, but they represent two pipeline products that could have meaningful clinical and financial implications for employer-sponsored health plans.

1. VDPHL01: Minoxidil 2.0

VDPHL01 is an oral, non-hormonal hair loss pill used to treat men and women.  The extended-release oral minoxidil tablet delivers hair regrowth benefits while avoiding the heart-related risks tied to immediate-release oral minoxidil. Phase 2/3 Study results released April 27, 2026 show strong efficacy signals, with robust hair growth seen in both once-daily and twice-daily dosing. Phase 3 studies are still being conducted.

If approved, VDPHL01 will become the first FDA-approved oral pill in nearly 30 years for treatment of pattern hair loss.2

VDPHL01 Estimated Market Availability: Late 2027 to early 2028. (pending successful completion of clinical trials and regulatory review).

Potential Financial Impact: Moderate to High

Plan sponsors should pay close attention because:

  • Oral medications are easy to prescribe and administer.
  • Clinical studies suggest meaningful hair regrowth benefits.
  • The eligible population includes both men and women.
  • Even a modest annual treatment cost can generate significant plan spend when multiplied across a large member population.

2. PP405: A Potentially Disruptive Stem Cell-Based Approach

PP405 represents a very different approach to treating hair loss. Rather than targeting hormones or improving blood flow, PP405 is designed to reactivate dormant hair follicle stem cells and stimulate new growth at the cellular level. The therapy is being developed for both men and women with pattern hair loss.

In a Phase 2 study, PP405 demonstrated a favorable safety profile with no treatment-related systemic adverse events reported. Phase 3 trials are expected to begin, although the product remains several years away from potential commercialization.3

Consumer excitement around PP405 has been substantial because it represents one of the first therapies seeking to regenerate hair growth by reactivating dormant follicles rather than slowing the progression of hair loss.

PP405 Estimated Market Availability: To be determined. The product remains in clinical development.

Potential Financial Impact: Moderate to High

From a pharmacy benefit perspective, this may be the more disruptive product.

If larger clinical trials confirm strong efficacy:

  • Demand could be significant.
  • Use could extend across a broad population of men and women.
  • Treatment may begin earlier in the disease progression process.
  • Specialty-drug pricing could place additional pressure on pharmacy budgets.
  • Physicians may view treatment as preventative rather than purely restorative.

How to Begin Assessing Your Rx Benefits Risk for Hair Loss Coverage

12-24 months before launch:

  1. Assess whether your current Rx and/or Medical benefits provide for hair loss treatments.
  2. For Benecard plan sponsors, have your brokers contact Benecard for the number of eligible members and their utilization based on any hair loss treatment usage from the most recent 12 months.
  3. Rethink Plan Design and Utilization Management Options for Hair Loss Category:
    1. Exclude
    2. Prior Authorization
    3. Step Therapy
    4. Member Cost Sharing

Although VDPHL01 and PP405 remain investigational therapies, both highlight a broader shift toward innovative treatments for highly prevalent lifestyle and quality-of-life conditions. For plan sponsors, the challenge will be balancing member access with responsible drug management tools in place prior to these drugs entering the marketplace.

Getting ahead of these therapies now allows organizations to thoughtfully design coverage and drug management strategies before high demand and additional cost increases arrive. To talk pharmacy benefit strategy, contact your Benecard Representative at talktous@benecard.com.

  1. https://medlineplus.gov/genetics/condition/androgenetic-alopecia/#frequency
  2. Veradermics’ Oral VDPHL01 Achieved Early, Consistent, and Robust Hair Growth in Positive Phase 2/3 ‘302’ Clinical Trial in Male Pattern Hair Loss | Mon, 04/27/2026 – 07:00
  3. https://www.dermatologytimes.com/view/reactivating-the-follicle-pp405-moves-toward-late-stage-trials-for-alopecia

FullSizeRender-8-scaled

NJ SHBP & SEHBP 2027 Rate Recommendations Released – What You Should Know

Last week, AON presented its recommended 2027 premium increases to the State Health Benefits Commission (SHBC) and the School Employees’ Health Benefits Commission (SEHBC) — and the numbers are substantial for both medical and Rx premiums:

Note: Active and Early Retiree premium rate changes shown above apply to both the legacy plan options and new plan options that were effective as of July 1, 2026.

Both the SHBP and SEHBP rate-setting analyses raise concerns that the proposed 2027 premium increases may not fully resolve the programs’ underlying financial challenges. In both cases, a portion of the increases is being used to repay prior funding obligations and rebuild depleted reserves, rather than solely cover projected healthcare costs.

Key Concerns

  • Premiums exceed projected costs:
    • SHBP: Recommended premiums are set 11.3% above projected costs for Actives and 34.5% above projected costs for Early and Medicare Retirees, including repayment of the remaining $90 million Chapter 86 obligation.
    • SEHBP: Recommended Active premiums are set 15.9% above projected claims costs, including a 4.2% margin to repay the projected $70 million Chapter 28 obligation plus an additional 11.7% to help build the Claims Stabilization Reserve (CSR).
  • Reserves remain below target:
    • Despite these significant increases, both programs project CSR balances of only 1 month of plan costs, well below the recommended 2-month target.
  • Future increases may be needed:
    • Actuaries for both programs caution that additional margin may be required, signaling the potential for further premium increases in 2027 and beyond.
  • Participation risk:
    • The analyses warn that rising costs will likely drive lower-risk employers out of the plans, increasing costs for those who remain and potentially creating additional financial pressure.
      • SHBP: This includes anti-selection assumptions of 5% in 2026, and 3% in 2027 reflecting the increased risk of employers choosing to leave the plan as a result of the additional cost.  This level of anti-selection may be insufficient if attrition from the plan is significant.
      • SEHBP: This includes anti-selection assumptions of 5% in 2026, and 4.75% in 2027 reflecting the increased risk of employers choosing to leave the plan.  Active enrollment is expected to decrease to 8.75% in 2027.

Bottom Line

While these increases are still recommendations and are not yet finalized, they reflect the ongoing financial instability in the state plans. Employers, employees, and retirees risk needing to absorb substantial premium increases, reduced benefits, and more out-of-pocket cost sharing with little confidence that it will be enough to meet targets and avoid future rate hikes—raising concerns about long-term affordability and sustainability.

Benecard will continue to update you on any further developments with the final 2027 rate actions as more information is released.

In the meantime, for plan sponsors enrolled in the SHBP or SEHBP, now is the time to start evaluating alternative options. In this volatile market, Benecard’s fixed-rate prescription benefit model can offer greater predictability and stability. Contact Richard Van Noord, Vice President of Sales, at Richard.VanNoord@benecard.com or (609) 651-5412 to learn about our unique prescription benefit solutions and to start a quote.

Sources:

1. Plan Year 2027 Rate Renewal Reports (recommendations):                                
https://www.nj.gov/treasury/pensions/rate-renewal.shtml

2. Aon’s SHBP “Plan Year 2027 Rate Setting Recommendation Analysis” Local Government draft report: https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/py2027-rate-setting-analysis-local.pdf

3. Aon’s “2027 SHBP Rate Setting Analysis” draft report presentation: https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/shbp-2027-rate-setting-analysis.pdf

4. View Aon’s SEHBP “Plan Year 2027 Rate Setting Recommendation Analysis” Education draft report: https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/py2027-rate-setting-analysis-education.pdf

5. Aon’s “2027 SEHBP Rate Setting Analysis” draft report presentation: https://www.nj.gov/treasury/pensions/documents/hb/rate-renewal/sehbp-2027-rate-setting-analysis.pdf

A roll of one hundred dollar bills sits among a row of prescription medication bottles. Photographed with a very shallow depth of field with the focus on the roll of money.

The Key to Predictable Pharmacy Costs for School Districts

Rising healthcare costs are forcing employers to make increasingly difficult financial decisions. Nowhere is this more evident than in public school systems. A recent BenefitsPRO article highlighted findings from a national survey of public school districts, where nearly every district reported significant budget pressures from escalating healthcare costs. Many now devote as much as 30% of their operating budgets to employee benefits, with prescription drugs—including specialty medications and GLP-1 therapies—identified as major cost drivers.

For benefit consultants and plan sponsors, the message is clear: controlling pharmacy benefit costs has become a necessary focus to improve overall healthcare affordability without sacrificing member care, particularly for organizations like school districts that must balance fiscal responsibility with contractual obligations and mission-driven outcomes.

An Independent PBM with a Proven Track Record of Cost Stability

Unlike many PBMs that are owned by pharmacy chains or health insurers, Benecard remains one of the few independent, standalone PBMs in the marketplace. For nearly 40 years, our singular focus has been helping employers and school districts achieve clinically sound, financially responsible prescription benefit solutions.

More importantly, Benecard stands apart with its 100% risk-free, guaranteed-cost prescription benefit arrangement. Benecard’s fixed monthly program charges—determined on a per employee per month (PEPM) basis—bundle prescription drug claims, rebates, administrative fees, clinical management programs, and excess loss insurance protection into one predictable monthly cost. This proven model eliminates all financial risk to the plan sponsor and offsets claim costs immediately with upfront rebates being accounted for beginning in the first month, while providing the budget certainty organizations—especially school districts—need in today’s volatile healthcare environment.

For districts navigating multi-year labor agreements and taxpayer-funded budgets, this level of predictability supports smarter financial planning without requiring ongoing renegotiation of employee benefits.  See our proven results by clicking here for our case study. To see what benefit consultants think of our services click here.

Proven Purchasing Power That Delivers Long-Term Results

Benecard also administers multiple Group Purchasing Arrangements (GPAs) that have been successfully operating for more than a decade. These established purchasing arrangements leverage collective buying power while maintaining flexibility for participating employer groups, including public sector entities like school districts. The results speak for themselves:

  • Stable rate action histories
  • Annual prescription drug trends consistently outperforming broader market averages
  • Sustainable savings—not just short-term savings strategies

For school districts, joining a GPA is particularly valuable. One of the key advantages of joining any GPA we administer is that there are no mandated benefit design changes—plan sponsors retain 100% autonomy over their benefits.

Therefore, rather than reacting to rising pharmacy costs with concessions at the bargaining table or cuts to student-facing investments, districts can adopt a structure that supports financial discipline and labor stability.

A Better Path Forward

As healthcare costs continue to rise, employers don’t have to accept unpredictable prescription benefit expenses as the new normal. With an independent PBM, guaranteed-costs, and proven savings strategies, Benecard helps organizations replace uncertainty with stability—protecting both employer budgets and employees’ access to quality pharmacy care.

For school districts in particular, this approach offers a path to regain control over one of the fastest-growing cost concerns, while respecting collectively bargained agreements and ensuring that more resources remain focused where they matter most: supporting educators and improving student outcomes.

If you’re looking for a better way to manage rising prescription benefit costs while bringing greater budget certainty, we’d welcome the opportunity to show you how Benecard’s proven approach can help. Please reach out to us at talktous@benecard.com to start the conversation.

Sources:

1: BenefitsPRO, “Rising health care costs force schools to cut benefits and tap reserves,” June 23, 2026, summarizing findings from the AASA and ASBO International report Rising Premiums, Falling Opportunities: The Budgetary Impact of Health Care Costs on School Districts.

Balance scale with green cash on left side and orange prescription bottle on right side

Get the Whole Picture on Level Funding: Look at The Advantages and Limitations

As plan sponsors and benefit consultants consider ways to reduce costs and gain flexibility for their health care benefits, the concept of level funding the prescription benefit is getting more attention. There are some advantages to level funding, as well as limitations, but a deeper dive also shows other funding arrangements may be better.

Level Funding Advantages

Level funding is a hybrid funding model that mixes elements of self-funding and may also include stop-loss protection. It features a fixed monthly cost billed to the plan sponsor, with total costs reconciled against actual claims at the end of the contract year. This funding arrangement can offer advantages over fully insured plans, such as the potential for refunds based on positive performance (at the PBM’s discretion) and benefit design flexibility. Conversely, this funding arrangement may offer some level of risk protection as an advantage over self-funding.

Level Funding Limitations

Level funding may include stop-loss insurance—either individual incident stop loss (per claim or per covered life), aggregate stop loss, or both—which help share the risk with the plan sponsor. This arrangement comes with several considerations that warrant careful evaluation:

  • If claims exceed the carrier’s stop loss liability at any point during the contract year, the plan sponsor will be 100% responsible for these additional costs, which would be beyond the fixed monthly costs they paid in that given contract year.
  • In some instances, the stop-loss carrier could impose limitations, such as adding an individualized high-cost deductible to the specific individual at risk or not covering the high-cost drug and leaving the plan sponsor with the financial risk to pay for it, referred to as lasering. 
  • If an adverse market event occurs, the PBM can increase the level-funded rates at any time in that given contract year or terminate the agreement with 30 days’ notice.
  • Reconciliation occurs six months after the end of the contract year to settle any differences in payments.

A Level Funding Alternative That Covers 100% of the Risk & Has A Proven Track Record

When it comes to guaranteeing the Rx benefit and taking on 100% of the risk, Benecard’s guaranteed cost, fixed rate program takes any potential concerns off the table by providing absolute budget predictability and returning 100% savings back to the plan sponsor. With a reliable and proven track record of working with public sector entities for nearly 40 years, our program offers:

  1. A fully guaranteed funding model, with no reconciliation or risk beyond the fixed monthly program charges (regardless of how high claims may rise), all underwritten specifically to the plan sponsor’s defined pharmacy benefit plan.
  2. No additional invoices for administration fees or clinical program fees, such as those for prior authorizations.
  3. 100% return of savings delivered back to the plan sponsor based on positive plan performance.
  4. Plan sponsors retain full autonomy of their benefits, without any lasering.
  5. Comprehensive clinical programs included as part of the standard program offering, at no additional charge.

With high trends in the industry along with more cost uncertainty, an offering that provides peace of mind without administration headaches, 100% return of savings for positive plan performance, monthly fixed program charges for budget predictability, and full plan sponsor control, is a strong alternative to the typical level funded or self-funded with back end stop loss models. Of course, we offer other funding arrangements to meet your needs.

If you would like to discuss more about how Benecard can help assist with 100% risk protection, budget predictability, plan design flexibility, and a return of savings offering, please reach out to us at talktous@benecard.com.

Sources:

https://npabenefits.com/disadvantages-of-level-funding

https://ethosbenefits.com/level-funded-health-insurance-pros-and-cons

https://www.hcaa.org/page/selffundingstoploss#:~:text=Stop%2Dloss%20insurance%20(also%20known,and%20aggregate%20stop%2Dloss%20coverage